
MEDICAL WEIGHT LOSS REALITY
>> Weight Management>> MEDICAL WEIGHT LOSS REALITY
MEDICAL WEIGHT LOSS REALITY
Medical Weight Loss in 2026: Evidence and Reality
The landscape of medical weight loss has transformed dramatically over the past five years, and 2026 represents a pivotal moment for how healthcare providers and patients approach obesity management. In my practice across Los Angeles, California, I’ve witnessed this evolution firsthand from outdated, often dangerous crash diet recommendations to sophisticated, evidence based interventions grounded in metabolic science and behavioral psychology. Health Forever is your ultimate guide to achieving long-term wellness and a balanced lifestyle.
Obesity affects nearly 42% of American adults according to 2026 CDC data, making it one of the most prevalent chronic health conditions in the nation. Yet it remains profoundly misunderstood. Most people assume weight gain results simply from overeating and lack of willpower. This reductive framing ignores decades of rigorous neuroscience demonstrating that obesity involves dysregulated appetite signaling, metabolic adaptation, hormonal disruption, and complex gene environment interactions.
My journey into medical weight loss began not as a career choice but as a necessity. After watching dozens of patients struggle with weight regain following bariatric surgery, I realized that surgery alone without comprehensive metabolic, behavioral, and pharmacological support often failed to produce sustainable results. This observation pushed me to develop integrated treatment protocols that address the biological roots of weight dysregulation.
Understanding Obesity as a Medical Condition, Not a Character Flaw
The brain’s appetite control systems centered in the hypothalamus and involving complex interactions between the prefrontal cortex, limbic system, and brainstem have evolved over millions of years to promote energy acquisition and storage. In ancestral environments where food scarcity posed constant threat, this system functioned optimally. In modern food environments saturated with highly palatable, calorie-dense ultraprocessed foods, this same system drives overconsumption.

The hormone leptin, secreted by adipose tissue, signals energy stores to the brain. In obesity, leptin levels elevate, yet the brain exhibits leptin resistance similar to insulin resistance in type 2 diabetes. Consequently, satiety signals diminish, hunger intensifies, and weight regain becomes neurobiologically inevitable without intervention.
Ghrelin, the “hunger hormone” secreted by the stomach, amplifies appetite signaling. After weight loss, ghrelin levels rise compensatorily, driving increased appetite and food-seeking behavior. This adaptation while protective against starvation sabotages weight loss maintenance. I’ve observed this phenomenon repeatedly in patients who achieve significant weight loss through diet alone; within 12-24 months, compensatory appetite increases precipitate weight regain.
Metabolic Adaptation and the “Set Point” Concept
Metabolic adaptation the body’s tendency to reduce energy expenditure in response to caloric restriction represents another fundamental challenge to sustained weight loss. When calories decrease, resting metabolic rate declines as the body attempts to preserve energy stores. This isn’t laziness or metabolic dysfunction; it’s an ancient survival mechanism.
Research from 2025-2026 has refined our understanding of the settling point theory, which posits that the body defends a particular weight range through integrated neuroendocrine adjustments. Successful weight loss requires not simply reducing calories temporarily, but fundamentally shifting this defended weight range through sustained behavioral, pharmacological, and sometimes surgical interventions.
The Role of Insulin and Glucose Metabolism
Hyperinsulinemia elevated fasting insulin levels despite normal blood glucose frequently accompanies obesity and predicts greater difficulty losing weight. Refined carbohydrates trigger excessive insulin secretion, driving glucose into cells and promoting fat storage while simultaneously suppressing satiety signals. This creates a vicious cycle: high insulin drives hunger, hunger drives overeating refined carbs, refined carbs spike insulin.
Addressing carbohydrate quality and timing, rather than simply restricting total calories, often proves more effective for weight loss in insulin resistant individuals. This explains why low-glycemic index diets frequently produce superior outcomes compared to standard low fat diets in clinical research.
Comprehensive Medical Weight Loss Assessment in 2026
When a patient presents to my Los Angeles clinic seeking weight loss support, I don’t immediately discuss calorie restriction or exercise. Instead, I conduct a thorough assessment addressing metabolic, endocrine, psychiatric, and behavioral dimensions of their weight trajectory.
This evaluation includes:
- Detailed weight history: When did weight gain begin? Were there discrete life events, hormonal changes, or medication initiations coinciding with escalating weight? Did weight loss attempts occur previously? If so, what methods, and what was the outcome?
- Dietary and eating pattern analysis: Not simple food logging, but understanding food preferences, eating triggers, meal timing, and the role food plays psychologically and socially
- Physical activity capacity and preferences: Realistic assessment of exercise tolerance, joint health, cardiovascular fitness, and activities the patient might actually sustain long-term
- Sleep and circadian rhythm assessment: Poor sleep and circadian misalignment independently predict weight gain through metabolic and appetite-regulating mechanisms
- Stress and mental health screening: Depression, anxiety, and chronic stress elevate cortisol and amplify appetite dysregulation
- Medications review: Antipsychotics, antidepressants, corticosteroids, and other agents commonly induce weight gain
Laboratory Assessment and Metabolic Screening
Blood work in 2026 medical weight loss practice extends well beyond simple chemistry panels. I routinely order:
Glucose Metabolism Panel:
- Fasting glucose, insulin, and calculated HOMA-IR (Homeostatic Model Assessment for Insulin Resistance) to quantify insulin resistance severity
- Hemoglobin A1C reflecting 3-month average glucose control
Thyroid Function:
- TSH, free T4, and sometimes free T3 and thyroid antibodies; hypothyroidism frequently contributes to weight gain and treatment resistance
Metabolic Biomarkers:
- Lipid panel assessing cardiovascular risk
- Liver function tests screening for fatty liver disease, common in obesity
- Vitamin D, B12, and iron levels, as deficiencies worsen metabolism and energy
Hormonal Assessment:
- Sex hormones (testosterone, estradiol) in appropriate clinical contexts, as hormonal dysregulation influences weight and appetite
- Cortisol patterns reflecting chronic stress effects
This comprehensive approach identifies modifiable contributors to weight gain, allowing targeted intervention.
Pharmacological Approaches to Medical Weight Loss
For patients considering or currently using Phentermine as part of their weight loss journey, understanding both its mechanism and proper access protocols is essential. Phentermine functions as a noradrenergic agent, increasing catecholamine activity in appetite-regulating brain regions while also modestly enhancing metabolic rate.
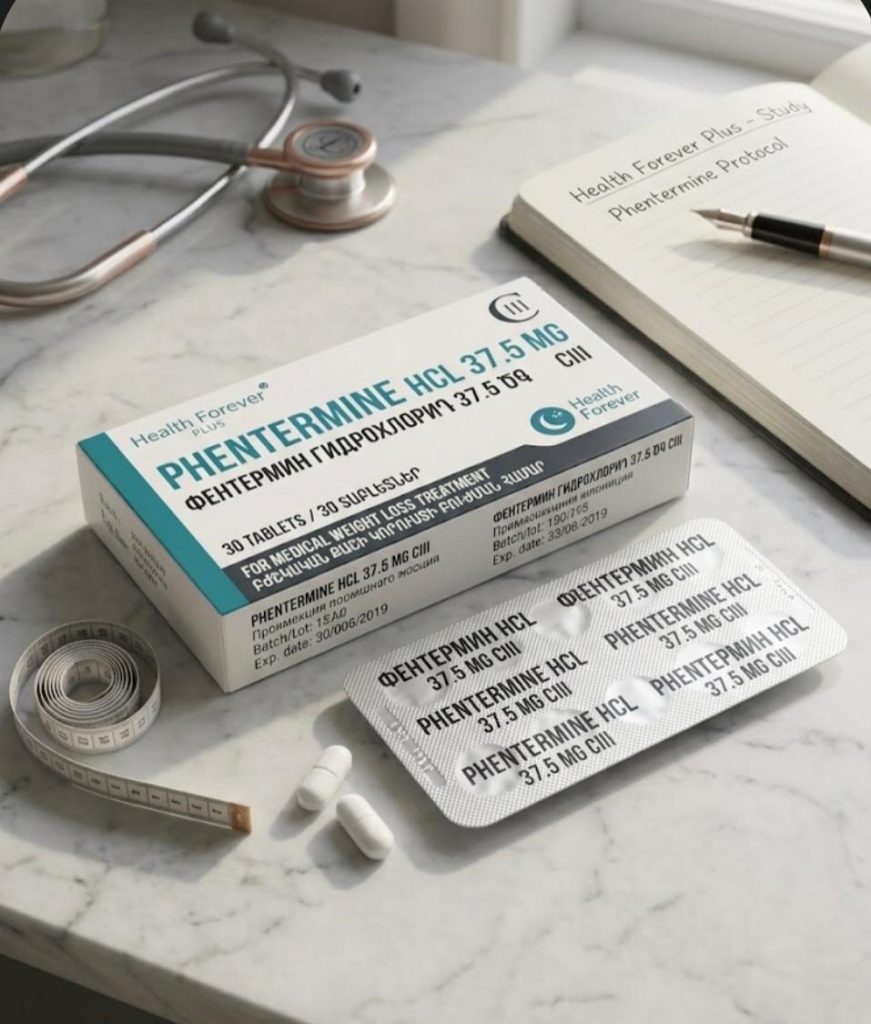
When looking to buy Phentermine, purchase Phentermine online, with a valid prescription, accessing this medication exclusively through verified, licensed pharmacies remains non negotiable. The distinction between legitimate prescription Phentermine access and illicit sources cannot be overstated. Getting Phentermine should only occur through DEA-registered pharmacies requiring proper medical evaluation and valid prescriptions from licensed healthcare providers.
I counsel patients extensively about Phentermine’s appropriate use: it’s most effective when prescribed for 12 weeks or less, though some patients benefit from intermittent use (medication holidays followed by reinitiating therapy). Combining Phentermine with comprehensive behavioral support, dietary modification, and activity increases produces superior outcomes compared to medication alone.
The risks accompanying inappropriate Phentermine use cardiovascular effects, insomnia, dependency potential underscore why safe, verified pharmacy access matters so profoundly. When patients purchase Phentermine online from unverified sources, they risk counterfeit products, underdosed medications, overdosed products (potentially dangerous), and complete absence of medical supervision. Legitimate pharmacies, by contrast, provide:
- Verification that prescriptions originate from licensed practitioners
- Quality assurance confirming authentic FDA-approved medications
- Proper dosing and packaging with accurate pharmaceutical standards
- Pharmacist consultation addressing potential drug interactions
- Records allowing your healthcare provider to monitor therapy
For those researching where to obtain Phentermine, major pharmacy chains (CVS, Walgreens, independent pharmacies verified through PharmacyChecker) and telemedicine platforms with proper medical oversight all represent legitimate avenues. These verified sources require prescription review by licensed providers, ensure genuine medications, and provide accountability. Never buy Phentermine from platforms offering it without prescription requirements or lacking clear pharmacy licensing information.
GLP-1 Receptor Agonists: A Paradigm Shift
The development of GLP-1 receptor agonists initially created for type 2 diabetes management has revolutionized obesity treatment. Agents like semaglutide and tirzepatide produce weight loss exceeding 15-22% of baseline body weight, far surpassing older sympathomimetics.
GLP-1 agonists work through multiple mechanisms: enhancing insulin secretion, slowing gastric emptying to prolong satiety, reducing appetite signaling in the brain, and potentially improving metabolic function. Patients describe taking GLP-1 medications as profound shifts in their relationship with food hunger simply diminishes, food cravings evaporate, and portion sizes feel naturally smaller.
I’ve observed these medications transform patients previously struggling with constant hunger and weight cycling. A 52-year-old patient of mine, despite decades of diet attempts and 240 pounds of excess weight, lost 85 pounds over 18 months on semaglutide combined with behavioral therapy and structured physical activity. More importantly, she’s maintained this loss 24 months later the real measure of success.
However, GLP-1 medications carry considerations: cost (often $1,000-1,500 monthly without insurance coverage), gastrointestinal side effects during titration, and weight regain risk if medications are discontinued without ongoing lifestyle support.
Combination Pharmacological Approaches
2026 evidence increasingly supports combining medications with different mechanisms. Phentermine plus topiramate (a weight loss-promoting anticonvulsant), for example, produces synergistic effects superior to either agent alone. Similarly, combining GLP-1 agonists with other agents in appropriate clinical contexts optimizes outcomes.
The key principle: pharmacotherapy works best as an adjunct to behavioral change, not a replacement for it.
Behavioral and Psychological Foundations
The most robust long-term weight loss outcomes occur when pharmacological interventions combine with evidence based behavioral therapy. Cognitive-behavioral therapy (CBT) for weight loss addresses the thoughts, emotions, and behaviors driving overconsumption.
Sessions focus on:
- Identifying and modifying food related cognitions (perfectionist thinking, all or nothing attitudes toward eating)
- Recognizing emotional eating triggers and developing alternative coping strategies
- Implementing behavioral strategies: self-monitoring, stimulus control, problem-solving
- Building self efficacy and motivation for sustained behavior change
- Addressing stress, sleep, and other lifestyle factors amplifying appetite dysregulation
From my clinical experience, patients who engage in concurrent behavioral therapy maintain weight loss far more effectively than those using medications or diet modifications alone. The behavioral work essentially retrains the brain’s reward systems and coping mechanisms.
Motivational Interviewing and Readiness for Change
Sustainable weight loss requires genuine readiness to change. Motivational interviewing a collaborative, non-judgmental approach exploring ambivalence about behavior change significantly improves outcomes compared to directive advice-giving.
Rather than telling patients they “must” eat differently or exercise more, motivational interviewing helps them articulate their own reasons for change, resolve conflicting feelings about behavior change, and develop intrinsic motivation. I’ve found this approach dramatically increases treatment engagement and success.
Nutritional Science and Dietary Approaches in 2026
While caloric balance remains fundamental to weight loss, 2026 nutritional science emphasizes food quality, macronutrient composition, and metabolic effects of different dietary patterns. Not all calories exert identical metabolic effects.
Protein intake, for instance, produces greater thermogenesis (energy expenditure during digestion) than carbohydrates or fat. Adequate protein approximately 1.6-2.2 grams per kilogram body weight reduces appetite, preserves lean muscle mass during weight loss, and improves metabolic function.
Fiber intake independently predicts weight loss and metabolic health. Dietary fiber slows gastric emptying, enhancing satiety, and feeds beneficial gut bacteria producing short-chain fatty acids that improve insulin sensitivity and reduce systemic inflammation.
Refined carbohydrates, conversely, spike blood glucose and insulin rapidly, triggering subsequent hunger and food-seeking behavior. Replacing refined carbohydrates with whole grains, legumes, and vegetables produces superior weight loss in insulin-resistant individuals.
Table 1: Comparative Nutritional Approaches for Weight Loss
| Dietary Approach | Weight Loss Potential | Metabolic Effects | Long-Term Sustainability | Best Suited For |
|---|---|---|---|---|
| Low-Fat Diet | Moderate (5-8%) | Reduced satiety; hunger rebound common | Poor without behavior support | Limited adherence populations |
| Low-Carb/Keto | High initial (10-15% first 6 months) | Rapid water loss; ketone production; appetite suppression | Variable; often regain when reintroducing carbs | Insulin-resistant individuals; short-term goals |
| Mediterranean | Moderate-High (7-12%) | Improved insulin sensitivity; anti-inflammatory; cardiovascular benefits | Excellent; most sustainable | Long-term health; cardiovascular disease prevention |
| Intermittent Fasting | Moderate (5-10%) | Potential metabolic benefits; simplified eating patterns | Fair-Good if incorporated into lifestyle | Metabolically flexible individuals; preference for simplified eating |
| Protein-Emphasis | Moderate-High (6-12%) | Enhanced thermogenesis; lean mass preservation; sustained satiety | Good; high protein adaptable to various cuisines | All populations; particularly effective with resistance training |
Practical Implementation and Adherence
The “best” diet is the one a person actually follows consistently. I spend considerable time understanding each patient’s food preferences, cultural dietary patterns, cooking capabilities, and realistic constraints before recommending specific dietary approaches.
For a patient with Mediterranean heritage who loves cooking traditional foods, Mediterranean diet recommendations resonate and show excellent adherence. For someone with severe time constraints, intermittent fasting’s simplicity might enhance compliance. Personalization, not prescription, drives success.
Physical Activity and Exercise Physiology
While exercise burns calories, its weight loss effects are often modest typically producing 2-3 pounds of weight loss beyond diet modifications alone. This disappoints patients expecting exercise alone to produce substantial weight loss. However, exercise’s metabolic and psychological benefits extend far beyond calorie expenditure.
Regular aerobic and resistance exercise improves insulin sensitivity, reduces visceral fat accumulation (the metabolic danger fat surrounding organs), improves cardiovascular function, enhances mood and stress resilience, and improves sleep quality. These adaptations support weight loss and health independent of pounds lost.
Resistance Training and Lean Mass Preservation
Resistance training during weight loss preserves lean muscle mass, preventing metabolic slowdown that typically accompanies caloric restriction. Additionally, muscle tissue is metabolically active maintaining muscle mass sustains higher resting metabolic rate.
I recommend resistance training 2-3 times weekly for all patients pursuing weight loss, particularly those using pharmacological support. This combination medication, behavioral therapy, adequate protein intake, and resistance training produces optimal outcomes.

Realistic Activity Recommendations
For sedentary or deconditioned patients, starting with walking 10-15 minutes daily, gradually increasing duration and intensity, proves more sustainable than aggressive exercise prescriptions that feel overwhelming.
In my Los Angeles practice, I acknowledge that not everyone enjoys traditional gym environments. Some patients prefer hiking, swimming, cycling, dance classes, or home-based routines. The optimal exercise is the activity someone will actually perform consistently.
Sleep, Stress, and Hormonal Optimization
Sleep loss independently drives weight gain through multiple mechanisms: elevated cortisol amplifying appetite signaling, reduced leptin production, increased ghrelin secretion, and impaired glucose regulation promoting cravings for refined carbohydrates. As discussed in our guide on Phentermine and weight management, metabolic stimulants can significantly impact sleep architectures, making modern insomnia management more critical than ever.”
Obtaining 7-9 hours of quality sleep nightly represents non-negotiable foundation for weight loss success. Patients who prioritize sleep optimization often report dramatically improved results from identical diet and exercise interventions.
Chronic psychological stress elevates cortisol, which promotes visceral fat accumulation, impairs glucose metabolism, and amplifies appetite for calorie-dense foods. Effective stress management through meditation, yoga, psychotherapy, or other methods meaningfully impacts weight loss outcomes.
Medical Weight Loss in Special Population
Bariatric surgery produces rapid, substantial initial weight loss; however, 30-50% of patients experience significant weight regain 3-5 years post-surgery without comprehensive post-operative support. Medications like GLP-1 agonists, combined with behavioral therapy and nutritional counseling, dramatically improve long-term outcomes after surgical weight loss.
Weight loss of just 5-10% improves insulin sensitivity and often improves or resolves type 2 diabetes. This modest weight loss achievable through behavioral modification and pharmacotherapy should be standard care for all overweight individuals with diabetes.
Women with PCOS exhibit significant insulin resistance and weight loss resistance. However, combination approaches addressing insulin resistance through lower glycemic index diet, regular exercise, inositol supplementation, and sometimes pharmaceutical agents like metforminproduce meaningful weight loss and symptom improvement.
Addressing Weight Loss Plateaus
Weight loss plateaus periods lasting weeks or months without further weight decline despite continued adherence occur in most patients. These reflect normal metabolic adaptation as the body adjusts to new energy intake levels.
Rather than viewing plateaus as failure, I reframe them as signals to adjust strategy. Options include: increasing physical activity intensity, increasing protein intake (enhancing satiety and thermogenesis), incorporating intermittent fasting or other dietary modifications, adding or adjusting pharmacotherapy, addressing sleep quality, or exploring stress reduction.
Most importantly, weight loss plateaus don’t mean weight regain is inevitable. Maintaining current weight while waiting for the body to readjust represents success.
Sustainable weight loss often requires lifelong behavioral and sometimes pharmacological support. This isn’t failure; it reflects the reality that obesity involves permanent neurobiological changes. The brain’s defended weight range doesn’t fully reset to a lower level successful weight loss maintenance requires ongoing adherence to modified eating patterns, regular activity, and often continued medication.
I discuss this explicitly with patients: weight loss is not a temporary project producing permanent results. Rather, sustained weight loss involves making sustainable lifestyle modifications that become normal rather than optional. The good news is that after 6-12 months of consistency, modified eating patterns and activity levels often feel less effortful, suggesting genuine behavioral change rather than willpower-dependent restriction.
Relapse Prevention and Long-Term Support
Identifying high-risk situations promoting weight regain holiday periods, stress, life transitions and developing proactive strategies (increased behavioral support, temporary medication adjustments, intensified activity) maintains weight loss.
Regular follow-up care, even when weight stability is achieved, provides accountability and allows early intervention if weight creep occurs.
Medical Weight Loss in Los Angeles: Specialized Considerations
Los Angeles presents unique opportunities and challenges for weight loss implementation. The year-round mild climate enables consistent outdoor activity hiking in nearby mountains, walking on beaches, outdoor fitness classes. However, car-dependent culture promotes sedentary patterns, and the restaurant and entertainment culture normalizes frequent consumption of calorie-dense foods.
Successful medical weight loss in Los Angeles often leverages outdoor activity opportunities while strategically navigating food-centric social situations.
Access to Specialized Care
Los Angeles contains numerous bariatric surgery centers, behavioral health providers, registered dietitians, and weight loss medicine specialists. Patients have access to comprehensive care if they seek it, though insurance coverage limitations sometimes restrict access to specialized services.
FREQUENTLY ASKED QUESTION
What’s the realistic weight loss expected from medical weight loss treatment?
Medical weight loss interventions typically produce 5-10% body weight reduction through behavioral modification and lifestyle changes alone, with medications adding an additional 3-7% reduction, and combination approaches often achieving 10-20% or greater weight loss over 12-24 months. Results vary substantially based on individual factors including starting weight, adherence, metabolism, and concurrent health conditions.
How long does medical weight loss treatment typically last?
Successful weight loss usually requires 6-12 months of active treatment, followed by long-term maintenance support that may extend indefinitely for patients with chronic weight dysregulation or obesity history. Many patients benefit from periodic medication use, behavioral therapy refreshers, and ongoing monitoring to maintain achieved weight loss and prevent regain.
Where can I safely purchase weight loss medications like phentermine and how do I know if a pharmacy is legitimate?
You should buy weight loss medications online exclusively through verified, NABP-accredited (National Association of Boards of Pharmacy) pharmacies that require valid prescriptions from licensed healthcare providers; major chains like CVS, Walgreens, and independent pharmacies displaying verification badges represent legitimate options, whereas platforms offering medications without prescription requirements or lacking clear licensing information pose serious risks including counterfeit products and identity theft.
What lifestyle changes matter most for sustainable weight loss?
The most impactful factors are adequate protein intake (supporting satiety and lean mass preservation), whole food emphasis over processed products, consistent resistance training 2-3 times weekly, consistent sleep of 7-9 hours nightly.